How Dr Cassar Diagnoses Atrial Fibrillation
Diagnosing AF starts with understanding your symptoms and their pattern. Are your palpitations constant or do they come and go? Do they last seconds, minutes, or hours? Are there triggers like alcohol, caffeine, or stress? These details help determine whether you have paroxysmal AF (episodes that come and go), persistent AF (continuous episodes lasting over a week), or permanent AF. During examination, feeling your pulse reveals the characteristic irregularly irregular rhythm of AF – the heartbeat has no pattern, distinguishing it from other rhythm problems. Blood pressure measurement and cardiovascular examination check for signs of heart strain, valve problems, or fluid retention that might complicate AF or indicate underlying causes.
An electrocardiogram (ECG) confirms AF by capturing the characteristic disorganised and irregular rhythm of AF. However, if your symptoms come and go, a standard ECG might miss episodes entirely. This is where ambulatory monitoring becomes valuable: a 24-hour Holter monitor records every heartbeat for a day, whilst longer-term event recorders (worn for weeks) capture infrequent episodes. Some patients experience palpitations weekly or monthly, making these extended monitors essential for diagnosis.
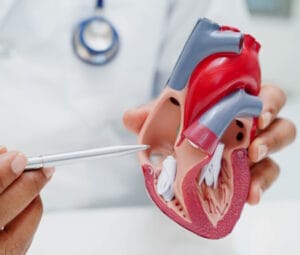
Blood tests check for reversible causes: an overactive thyroid can trigger AF, whilst kidney problems or electrolyte imbalances might complicate treatment. Dr Cassar’s imaging expertise becomes particularly important during echocardiography – detailed ultrasound assessment identifies whether AF has caused heart muscle weakening, whether valve disease might be triggering AF, or whether the heart’s upper chambers have enlarged (suggesting longstanding AF). These findings directly influence treatment decisions.
Once AF is confirmed, stroke risk assessment becomes crucial. This is done by using a validated risk score that combines age, medical conditions, and previous strokes – determining whether blood-thinning medication is recommended. Higher scores mean higher stroke risk and clearer benefit from anticoagulation.
However, blood thinners increase bleeding risk, so Dr Cassar also considers factors like previous bleeding episodes, falls risk, and kidney function. This balancing act between preventing stroke and avoiding bleeding complications requires individualised assessment rather than rigid protocols. For some patients, additional imaging with transoesophageal echocardiography (an ultrasound probe passed down the gullet to look directly at the heart) may be needed before cardioversion procedures to ensure no clots have already formed.
Dr Cassar’s approach integrates all these findings – symptom pattern, ECG and monitoring results, blood tests, detailed cardiac imaging, and risk scores – to develop a comprehensive treatment plan addressing stroke prevention, rhythm or rate control, and any underlying cardiac conditions contributing to your AF.
Diagnostic assessments