If your blood pressure readings remain above target despite taking prescribed medication, a review usually starts with the reading itself, not the tablets. A clinician will check how and when readings were taken, look at an average from several occasions rather than one number, and consider your individual target before deciding whether anything about the treatment plan needs to change. A single high reading, taken after a rushed walk or a stressful morning, is not the same as a pattern that holds across several days.
One reading is not the same as a trend
Blood pressure varies naturally through the day. It differs between first thing in the morning and the evening, and it rises temporarily with pain, cold, caffeine, a full bladder or talking during the measurement. A single elevated figure, even a notably high one, does not necessarily mean the medication has stopped working.
What matters more is the average across a series of readings taken under reasonably consistent conditions. This is partly why clinic readings and home readings can differ, sometimes in either direction: some people have higher readings in a clinic setting, often called the white-coat effect, while others show the reverse pattern, known as masked hypertension, where readings away from the clinic run higher than a brief appointment reveals. Where clinic and home readings disagree, a period of ambulatory monitoring, where a small cuff records blood pressure automatically over 24 hours, can help clarify the true picture. The 24-hour blood pressure monitoring page explains how that test works.
Getting the measurement right
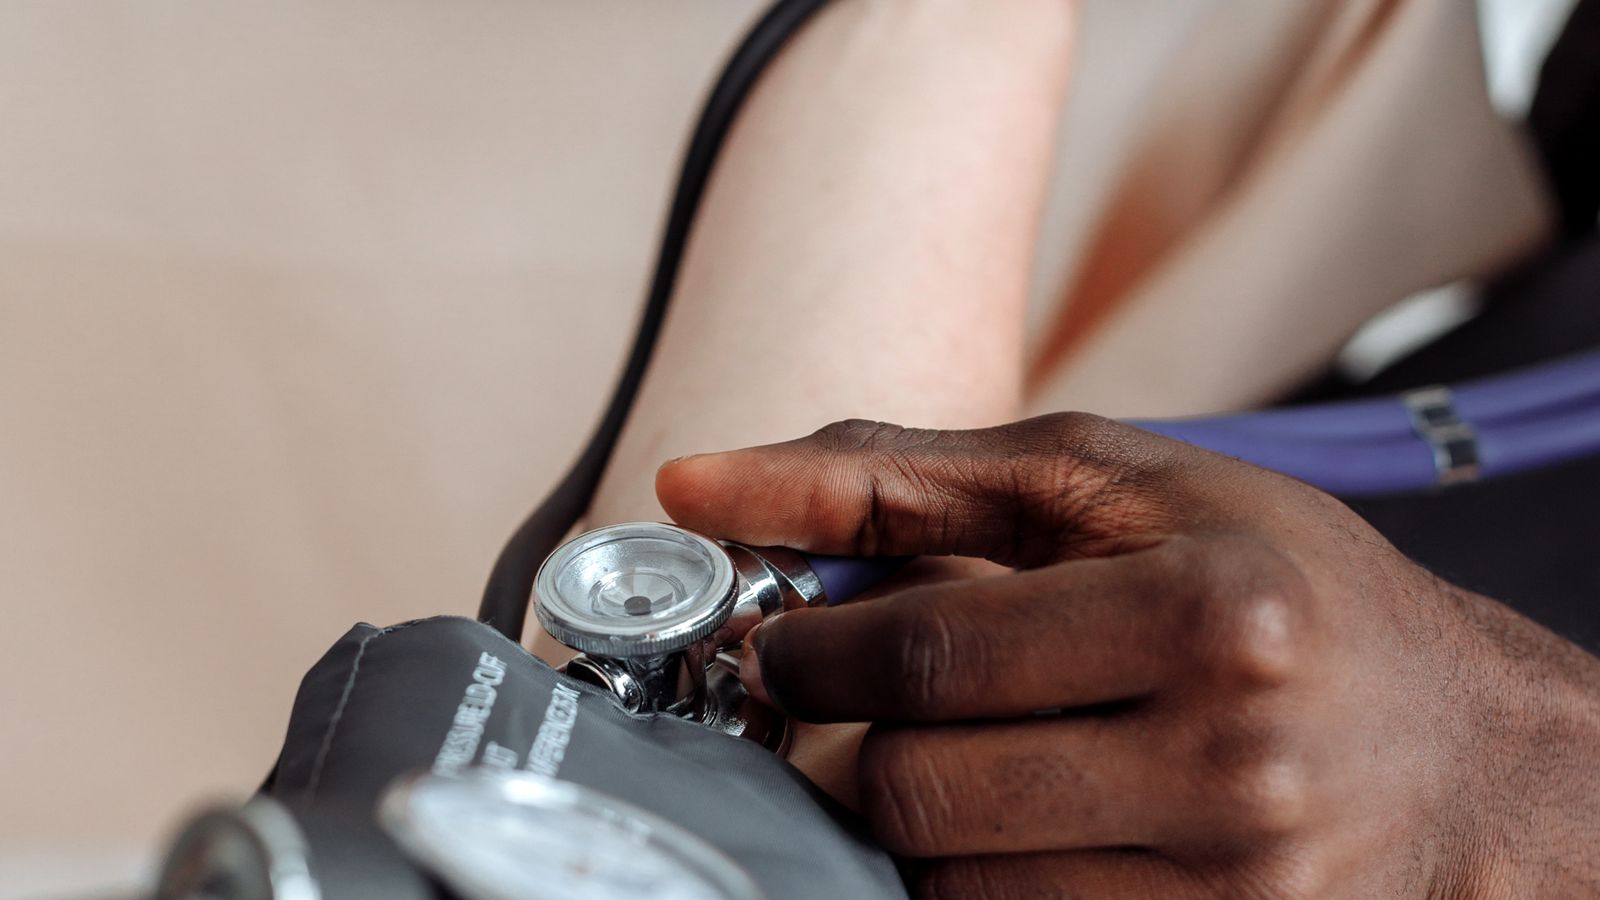
Technique affects the result more than people often expect, and this is not about anyone doing something wrong. A cuff that is the wrong size for the arm, an unsupported arm, crossed legs, or measuring immediately after rushing in from outside can all shift the reading.
Before assuming a pattern of readings is wrong, it is worth checking the basics: sit quietly for a few minutes beforehand, rest the arm on a support at roughly heart height, use a cuff sized correctly for your arm, and take the measurement on a validated device. If you are unsure whether your readings are reliable, bring the device itself, along with a record of readings and the times they were taken, to a review so the technique and equipment can be checked alongside the numbers.
None of this is about self-correcting or adjusting your own medication based on home readings.
When to seek urgent help
Most persistently raised blood pressure readings are not a medical emergency, and a routine review is the right next step. A few situations call for prompt attention instead.
Call 999 for sudden, persistent chest pain, especially with breathlessness, sweating or feeling generally unwell, as this can suggest a heart attack. Do not drive yourself to hospital.
If you have a very high reading, or any new symptom that worries you, seek prompt professional assessment rather than waiting for your next scheduled appointment, whatever the number itself happens to be. Your GP, NHS 111 or an out-of-hours service can assess this and decide what, if anything, needs to happen quickly. This kind of urgent assessment is not something a routine private cardiology appointment is designed to replace; if something feels seriously wrong, use NHS emergency or urgent care routes first.
Possible contributing factors
If a genuine pattern of raised readings is confirmed, a review usually works through a short list of possibilities rather than jumping straight to a change in prescription. It typically starts with confirming that the readings themselves are representative, then looks at how well the current medication is being tolerated and whether anything else, including other prescribed medicines or over-the-counter products, might be working against control. Depending on what emerges, more targeted further assessment may follow for a specific reason, rather than as a routine step for everyone.
The broader set of possible causes, and how hypertension is normally managed, is covered on the hypertension page. This article focuses on the narrower question of what gets looked at when treatment does not seem to be working as expected.
When it becomes "resistant" hypertension
The term resistant hypertension has a specific meaning in clinical guidance. It describes blood pressure that stays above target despite taking the best-tolerated doses of three particular medicines used together. In plain terms, these typically work in different ways: one relaxes blood vessels by acting on a hormone pathway involving the kidneys (an ACE inhibitor or an ARB), one relaxes the blood vessel walls directly (a calcium-channel blocker), and one helps the kidneys clear excess salt and fluid (a thiazide-like diuretic). The term does not describe someone on a single tablet whose pressure has not yet settled, a dose only recently started, or one isolated high reading.
Before resistant hypertension is confirmed, the usual approach is to check the pattern with readings taken outside the clinic, such as home or ambulatory monitoring, check standing blood pressure when clinically indicated, and talk through how medication is actually being taken day to day. Missed doses, side effects or timing issues are common and easily addressed once identified, and raising this is a routine part of a thorough review rather than any kind of blame.
Tests that may be used, and ones that are not automatic
An ECG, a simple recording of the heart's electrical activity, may help assess whether sustained high blood pressure has affected the heart, when there is a clinical reason to check. It is not something every patient with a raised reading automatically needs. An echocardiogram, an ultrasound scan of the heart, is used even more selectively, only when there is a specific reason to look more closely at heart structure or function. Neither test follows on automatically from a single reading; the timing of either depends on the individual picture rather than a fixed schedule.
Preparing for a review
A review tends to be more useful when there is clear information to work from. Before a routine appointment, it helps to gather:
- A series of readings over several days, with dates and times, rather than a single figure
- The home monitor itself, so the cuff size and device can be checked
- A full list of current medicines and doses, including anything bought over the counter or taken as a supplement
- Any previous blood pressure results or monitoring reports you may have
This allows the conversation to focus on the actual pattern, rather than reacting to one figure taken in isolation.
Taking this to a review
Outside an emergency, a pattern of readings that has stayed above target is best discussed at a planned appointment, where the full picture, including technique, timing and any new medicines, can be looked at together.
Where a cardiology opinion feels appropriate, perhaps because readings have remained unexpectedly high despite reasonable treatment, or because of other heart-related concerns alongside the blood pressure itself, patients can arrange a cardiology appointment with Dr Mark Cassar to review the pattern in full.
Frequently asked questions
Does a single high home reading mean my medication has stopped working?
Not usually. Blood pressure varies naturally during the day, and one reading can be affected by stress, caffeine, pain or how it was measured. The average across several consistent readings matters more than any single figure, which is why a pattern is reviewed rather than one number in isolation.
Why might my blood pressure differ between home and the clinic?
This is common and can happen in either direction. Some people have higher readings in a clinic setting, known as the white-coat effect, while others have higher readings away from the clinic, known as masked hypertension, that a brief appointment can miss. When the two disagree, a period of ambulatory monitoring can help clarify the underlying pattern.
Could something other than my blood pressure tablets be the cause?
It's possible. A review usually starts by confirming the readings themselves, then looks at how well the current medication is tolerated and whether other medicines or over-the-counter products might be working against control. Further, more targeted assessment follows only where there is a specific reason for it, rather than as a routine step for everyone.
What does "resistant hypertension" actually mean?
It describes blood pressure that stays above target despite well-tolerated doses of three types of medicine working together: one acting through a kidney-related hormone pathway, one relaxing the blood vessel walls directly, and one helping the kidneys clear excess salt and fluid. It is confirmed only after checking readings taken outside the clinic, standing blood pressure where indicated, and how medication has actually been taken, and is a different situation from early treatment that has not yet settled.
Will I definitely need a heart scan if my readings stay high?
No. An ECG may help assess whether high blood pressure has affected the heart when there is a reason to check, but an echocardiogram is used only when there is a specific reason to look more closely, not as a routine test for every raised reading.